Friday, December 16, 2011

Controversies in COPD treatment

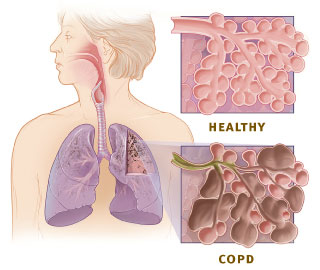
Chronic obstructive pulmonary disease (COPD) is a chronic disorder with high mortality rates (one of the top 5 causes of death).

COPD is expected to rise to the third leading cause of death worldwide by 2030. More than 25% of COPD patients have never been smokers.

Some important controversies in COPD management still exist:

- The classic way to define COPD has been based on spirometric criteria, but more relevant diagnostic methods are needed that can be used to describe COPD severity and comorbidity

- Initiation of interventions earlier in the natural history of the disease to slow disease progression is debatable

- There are controversies about the role of inhaled corticosteroids (ICS) in the management of COPD

- Long-term antibiotics for prevention of exacerbation have had a resurgence in interest

New drugs are urgently needed for management of COPD exacerbation.

COPD is a complex disease and consists of several phenotypes that in future would guide its management.


Asthma Inhalers (click to enlarge the image). Advair and Symbicort are FDA-approved for treatment of COPD in the U.S.

References:

Controversies in treatment of chronic obstructive pulmonary disease. Prof Klaus F Rabe MD a , Jadwiga A Wedzicha MD b. The Lancet, Volume 378, Issue 9795, Pages 1038 - 1047, 10 September 2011.

New insights into the immunology of chronic obstructive pulmonary disease. The Lancet, Volume 378, Issue 9795, Pages 1015 - 1026, 10 September 2011.

COPD—more vigorous research needed. The Lancet, Volume 378, Issue 9795, Page 962, 10 September 2011.

Diagnosis and Management of COPD - Current Guidelines

Image source: Enlarged view of lung tissue showing the difference between healthy lung and COPD, Wikipedia, public domain.

Wednesday, December 14, 2011

Stress fractures

From a 2011 review in the journal American Family Physician:

Stress fractures are common injuries in athletes and military recruits. These typically affect lower extremities.

Symptoms of stress fractures

Stress fractures should be considered in patients who present with tenderness and/or edema after a recent increase in activity or repeated activity with limited rest.

The Barefoot Professor says barefoot running could minimize injuries although this approach is still experimental:


The differential diagnosis of stress fractures includes:

- tendinopathy
- compartment syndrome
- nerve or artery entrapment syndrome
- medial tibial stress syndrome (shin splints) can be distinguished from tibial stress fractures by diffuse tenderness along the length of the posteromedial tibial shaft and a lack of edema

Diagnosis of stress fractures

When stress fracture is suspected, plain radiography should be obtained initially and, if negative, may be repeated after 2-3 weeks for greater accuracy.

If an urgent diagnosis is needed, triple-phase bone scintigraphy (bone scan) or magnetic resonance imaging (MRI) should be considered. Both modalities have a similar sensitivity, but MRI has greater specificity.

Treatment of stress fractures

Treatment of stress fractures consists of:

- activity modification - nonweight-bearing crutches if needed for pain relief
- analgesics
- pneumatic bracing

After the pain is resolved, patients may gradually increase their level of activity.

Surgical consultation may be appropriate for patients with:

- stress fractures in high-risk locations
- nonunion
- recurrent stress fractures


Related reading:

The Barefoot Running Revolution - INFOGRAPHIC  http://goo.gl/7SUGs

Best Tweets - Selection of Twitter Favorites


The inclusion of a Twitter update (tweet) in Best Tweets - Selection of Twitter Favorites does not represent endorsement or agreement of any kind. If you are included in this post but you would like to have your tweet removed for any reason, please email me and will comply with your request the same day.

Tuesday, December 13, 2011

Factors that Promote Positive Adaptation to Stress and Adversity

The phenomenon of resilience reflects positive adaptation despite contexts of risk, adversity, or trauma.

Factors that promote positive adaptation to stress and adversity include the following:

- self-esteem
- optimism
- internal control
- coping aimed at acceptance
- coping aimed at seeking emotional support
- social contacts


Tips for managing stress (2-minute BBC video):

- Take a few deep breaths
- Get plenty of exercise
- Socialize - don't stress alone, talk to someone and have a laugh
- Get out - go to the park

Read more: http://www.bbc.co.uk/scotland/brainsmart

References:

Psychological and Social Factors that Promote Positive Adaptation to Stress and Adversity in the Adult Life Cycle. M. Guadalupe Jiménez Ambriz, María Izal and Ignacio Montorio. Journal of Happiness Studies, 2011.

Monday, December 12, 2011

Acute pyelonephritis in women (2011 review)

This is a 2011 review from the official journal of the AAFP, American Family Physician:

Acute pyelonephritis is a bacterial infection of the renal pelvis and kidney most often seen in young women.

Symptoms of acute pyelonephritis

Most patients have fever, although it may be absent early in the illness. Flank pain is nearly universal.

Tests for acute pyelonephritis

A positive urinalysis confirms the diagnosis.

Urine culture should be obtained in all patients to guide antibiotic therapy if the patient does not respond to initial empiric antibiotic regimens.

Escherichia coli is the most common pathogen in acute pyelonephritis. In the past decade, there has been an increasing rate of E. coli resistance to extended-spectrum beta-lactam antibiotics.

Imaging, usually with contrast-enhanced CT is not necessary unless there is:

- no improvement in the patient's symptoms
- symptom recurrence after initial improvement

Treatment of acute pyelonephritis

Outpatient treatment is appropriate for most patients.

Oral fluoroquinolone is the initial outpatient therapy if the rate of fluoroquinolone resistance in the community is less than 10%. If the resistance rate exceeds 10%, an initial IV dose of ceftriaxone or gentamicin should be given, followed by an oral fluoroquinolone regimen.

Oral beta-lactam antibiotics and trimethoprim/sulfamethoxazole (TMP-SMX (Bactrim) are inappropriate for therapy because of high resistance rates.

References:

Diagnosis and treatment of acute pyelonephritis in women. Colgan R, Williams M, Johnson JR. Am Fam Physician. 2011 Sep 1;84(5):519-26.
Nephrology Cases

Friday, December 9, 2011

UpToDate is the most read medical reference tool - how did Harrison's, Cecil's, etc. manage to lose that war?

This the summary of my Twitter discussion with an academic nephrologist (by the way, the founding editor of UpToDate is also a nephrologist):

@DrVes: UpToDate is likely the most read medical reference tool, at least in the U.S. - how did Harrison's, Cecil's, etc. manage to lose that war?

@kidney_boy (Joel Topf): Reasons for UpToDate winning: Harrison's had no search, and an editorial style that told you about disease but not how to treat it

@DrVes: Exactly. It's amazing that those publishing companies didn't realize that they shipped "malfunctioning" product for years, and never fixed it.

@kidney_boy (Joel Topf): Harrison's is the great preclinical prof teaching pathophysiology, UpToDate is the smart clinician teaching you how to care for the patient with EBM.

@DrVes: UpToDate now has sections on pathophysiology, some of them quite good, check T-cells types, for example. Unfortunately, a lot of medical students get their basic pathology knowledge from Wikipedia nowadays. Just go to the library section where medical students are and have a look at the monitor screens during study time.

@kidney_boy (Joel Topf): Remember Harrison's is the youngest of the medical texts, it won by having regional approach (headache rather than CNS) to organization.

@DrVes: Classic-style textbooks (e.g. Harrisson's) feel like "half-book" nowadays. The doctors in training often find themselves asking "Where is the second part with treatment, updates, etc.?"

Related reading:

Review of the much anticipated UpToDate iPhone app, arguably the most read medical reference tool. iMedicalApps.com.
Are You Dependent on UpToDate for Your Clinical Practice?
"With UpToDate, students and interns may be as capable of teaching the resident (or attending) as visa versa"
Study: UpToDate More Likely than PubMed to Answer Patient Care Questions

Comments from Google Plus:

Neil Mehta - Ves one of the most useful aspects of Harrison's is/was the approach to symptoms. This is the first 100 or so pages of Harrison's. Understanding this can be a huge help in becoming a good clinician. It is pretty dense reading but internal medicine residents can benefit from spending time on this. Agree UpToDate is a tremendous resource. One thing to remember about U2D is that sections can be written by one author and this does run a risk of bias creeping in (no different than textbooks) but readers should learn to look at other sources/primary literature when necessary.

Ves Dimov - Right. UpToDate is far from perfect but it is very time efficient. It provides quick actionable info within 5-10 minutes of conducting a search. The depth of the content is limited by the person who wrote that particular article, of course.

Robert Silge - Yes, but by and large the people writing that content are qualified to do so. It is to medical textbooks what Wikipedia is to general reference books. Updates faster, to the point, and has info on (almost) everything. Its depth may be lacking, but for clinical practice I doubt the benefits of reading through primary literature is worth the time spent doing it for most endeavors.

And frankly for your first foray into a field, as a med student for example, Wikipedia is a darned useful place to start.

Ves Dimov - And that's why UpToDate is most users' favorite resource. One of the few drawbacks is the price though, $495 per year.

Robert Silge - Wonder how many people pay for it out of pocket vs use an institutional login?

Gary Levin - Up to date is like rounding with your attending or professor with instantaneous gratification. Harrison belongs in the library or for a second year med student to learn the language.
Friday, December 2, 2011

Headache subtypes: 30-year prospective cohort study

This BMJ study included 590 people aged 19-20 from a cohort of 4,500 residents of Zurich, Switzerland, interviewed 7 times across 30 years of follow-up.

The one-year prevalence of subtypes of headache were:

- 1% (female:male ratio of 2.8) for migraine with aura
- 11% (female:male ratio of 2.2) for migraine without aura
- 11% (female:male ratio of 1.2) for tension-type headache

The cumulative 30-year prevalence of headache subtypes were:

- 3% for migraine with aura
- 36% for migraine without aura
- 29% for tension-type headache

Despite the high prevalence of migraine without aura, most cases were transient and only 20% continued to have migraine for more than half of the follow-up period.

There was a substantial crossover among the subtypes and no specific pattern of progression.

The longitudinal overlap among subtypes of headache shows the developmental heterogeneity of headache syndromes.

References:

Magnitude, impact, and stability of primary headache subtypes: 30 year prospective Swiss cohort study. BMJ, 2011.

Image source: Openclipart.org, public domain.